Resources
Mental Health Content Marketing with Clinical Review
Mental health content marketing is the systematic creation and clinical verification of educational resources designed to guide patients into outpatient therapy, psychiatry, and specialized behavioral healthcare. Operating in sensitive clinical categories requires editorial governance that protects vulnerable searchers while satisfying rigorous medical search standards. When clinics align clinical oversight with privacy-safe intake systems, educational publishing becomes a sustainable driver of qualified patient evaluations.
By Mike Hulick, Founder, Marketing Powered

Clinical Governance and Quality in Behavioral Health Content
Generic digital marketing strategies routinely fail when applied to psychiatric practices and behavioral health clinics. Outpatient mental health operations operate under intense regulatory scrutiny, clinical ethics, and strict consumer trust requirements. When a commercial business publishes low-quality blog posts about consumer products, the operational downside is limited to wasted production spend. When a behavioral health clinic publishes unvetted medical advice regarding severe depressive episodes, medication titrations, or panic symptoms, the clinical risk falls directly on the patient, and the reputational liability falls on the provider.
The operational core of clinical content governance requires moving editorial responsibility out of isolated marketing teams and into a formalized medical review protocol. In this workflow, licensed professionals, such as psychiatrists, psychiatric mental health nurse practitioners, licensed clinical social workers, or clinical psychologists, review every informational draft before publication. The clinical reviewer verifies diagnostic criteria against established reference manuals, checks that medication references reflect standard psychiatric practices, and ensures that crisis helpline information is prominently positioned when content touches acute self-harm, trauma, or severe psychiatric distress.
Search platforms evaluate medical and psychiatric resources under strict quality frameworks often classified as Your Money or Your Life topics. To assess whether content offers sufficient experience, expertise, authoritativeness, and trust, search algorithms inspect verified author credentials, visible medical review stamps, citations to peer-reviewed clinical literature, and institutional credibility. Mental health marketing content produced without clinical review signals a lack of professional authority. This gap depresses organic visibility and deters prospective patients who need reassurance regarding a clinic's diagnostic capability.
Establishing clinical governance also enforces clear ethical boundaries in patient messaging. Informative psychiatric publishing must describe symptoms, differential diagnoses, and evidence-based treatment modalities without diagnosing the reader or offering unfounded clinical reassurance. The text should clarify the typical course of evidence-based modalities, including cognitive behavioral therapy, dialectical behavior therapy, transcranial magnetic stimulation, or psychiatric medication management, while setting realistic timelines for therapeutic response. By institutionalizing clinical governance, multi-provider practices ensure that every published resource serves as a safe, accurate, and defensible point of entry for patient care.

Mapping Mental Health Search Intent Across Patient Journeys
Prospective patients search differently depending on their diagnostic clarity, emotional readiness, and urgency. A successful content program avoids producing uniform wellness advice and instead maps distinct clinical assets to the specific cognitive stage of the searcher. Behavioral health search journeys fall into two broad stages: diagnostic exploration and treatment navigation.
Diagnostic exploration occurs when individuals or their family members encounter distressing emotional, cognitive, or behavioral symptoms without knowing the underlying cause. Search queries in this stage concentrate on functional impairments, symptom timelines, and differential distinctions. For example, a prospective patient rarely begins by searching for a specific psychiatric billing code or specialized clinic. Instead, they search queries such as why panic attacks happen at night, physical symptoms of high-functioning anxiety, or executive dysfunction versus adult attention-deficit/hyperactivity disorder.
Content built for diagnostic exploration must prioritize objective psychoeducation. The page should outline clinical symptom clusters, normalize the process of seeking formal psychiatric evaluation, and guide the reader away from self-diagnosis. These resources should never use aggressive conversion hooks or high-pressure calls to action. Searchers in an exploratory state require steady, credentialed guidance that outlines standard evaluation procedures and introduces the practice as a trusted community resource.
Treatment navigation occurs when an individual understands their diagnosis and seeks active medical intervention. Searches in this stage include queries like adult ADHD psychiatric evaluation near me, intensive outpatient programs for adolescent depression, or TMS therapy for treatment-resistant depression. Content addressing treatment navigation requires clinical precision, logistical clarity, and operational transparency. These pages must detail treatment protocols, session frequency, clinician specializations, accepted commercial insurance plans, and the intake evaluation timeline.
When structuring psychiatry content marketing for specialized services, practices must address the practical questions that cause prospective patients to abandon intake. For specialized modalities such as Esketamine nasal spray administration, deep transcranial magnetic stimulation, or child and adolescent medication management, the content must explain the on-site monitoring protocol, clinical eligibility criteria, and administrative clearance steps. Clarifying these operational details early removes emotional friction, builds institutional transparency, and qualifies inquiries before intake coordinators process the initial call.
For organizations looking to scale this structured intent mapping across regional locations, integrating local search architecture is essential. Discover how our team configures multi-location search structures through targeted mental health SEO strategies that align local clinical intent with community demand.
Service Line Architecture for Outpatient and Psychiatry Practices
Multi-provider outpatient clinics and specialized psychiatric networks cannot rely on generic service overviews. When a practice lumps psychotherapy, medication management, psychological testing, and adolescent care into a single page, search engines struggle to understand topical depth, and prospective patients fail to find answers specific to their condition. A scalable content architecture requires dedicated, interconnected hubs built around core clinical service lines.
Every major clinical specialty requires a foundational service landing page supported by detailed diagnostic guides, patient preparation resources, and clinical FAQ hubs. Consider an outpatient psychiatry practice offering medication management alongside interventional treatments. The site architecture should establish clear hierarchies:
This structural separation provides three distinct operational advantages. First, it establishes topical authority by proving to search crawlers that the clinic maintains comprehensive clinical depth within each therapeutic modality. Second, it mirrors the operational reality of the practice. Patients seeking medication evaluations for adult bipolar disorder have entirely different clinical questions, intake workflows, and provider needs than parents seeking comprehensive neuropsychological assessments for an adolescent.
Third, an explicit service line architecture streamlines provider attribution. Within multi-specialty practices, incoming appointments must route directly to the appropriate clinical team, whether that involves medical doctors, nurse practitioners, licensed professional counselors, or child specialists. When service line hubs include dedicated provider bios highlighting specific clinical training, board certifications, and published research, patient confidence increases. Connecting detailed clinical explanations directly to the clinicians who deliver care creates a transparent continuum that bridges digital inquiry and clinical intake.
Free Audit
Want a straight read on where your budget is leaking?
Privacy Architecture and Regulatory Constraints in Mental Health Promotion
Marketing standard commercial services allows organizations to deploy aggressive tracking scripts, behavioral retargeting campaigns, and third-party demographic profiling. In mental health and psychiatric care, these consumer tracking techniques violate federal regulatory guidance, platform advertising rules, and clinical confidentiality. Practice leaders must design an acquisition architecture that respects health privacy mandates while maintaining visibility into appointment volume.
Search and social advertising platforms maintain strict policies prohibiting personalized targeting based on sensitive personal health conditions. For instance, Google Ads policy on personalized advertising strictly forbids advertisers from creating remarketing audiences, retargeting lists, or personalized ad segments based on a user's physical or mental health status, including clinical depression, addiction, sexual health, or psychiatric conditions. When clinics attempt to set up retargeting tags to follow visitors who viewed a depression treatment page, they risk ad account suspensions and regulatory investigation.
Furthermore, federal regulators have sharply curtailed the use of unauthenticated tracking pixels on digital health properties. The U.S. Department of Health and Human Services (HHS) Office for Civil Rights issued specific regulatory guidance concerning the deployment of online tracking technologies by covered entities. According to the HHS bulletin on online tracking technologies, covered entities cannot share protected health information (PHI)—including IP addresses, appointment scheduling selections, or specific health service inquiries—with third-party tracking vendors without valid HIPAA business associate agreements or explicit patient authorizations.
To operate safely within these regulatory boundaries, behavioral health groups must implement a privacy-preserving content architecture:
- Eliminate Third-Party Tracking on Sensitive Content: Remove client-side pixels provided by consumer social networks and advertising platforms from educational blog pages, symptom assessments, and appointment request forms.
- Deploy Server-Side Privacy Filtering: Route necessary analytics events through internal server-side tracking pipelines that strip out personal identifiers, IP addresses, and specific URL query parameters before transmitting aggregate performance metrics.
- Isolate Clinical Intake Portals: Ensure that all electronic health record (EHR) scheduling widgets, patient portals, and direct messaging tools operate in secured, encrypted environments covered by comprehensive business associate agreements with vendors.
- Comply with Platform Verification Standards: For behavioral health facilities running paid acquisition alongside organic search, maintain required third-party verifications. Under the Google Ads healthcare advertising policy, facilities advertising addiction treatment or sensitive pharmaceutical interventions must obtain LegitScript certification before serving ads.
Marketing Powered was built specifically for Google's sensitive healthcare vertical, where retargeting is not permitted. Our operations rely on owned, local AI infrastructure for HIPAA-aware inference, giving multi-location groups complete control over proprietary data without exposing patient interactions to public cloud models. Operating ethically within behavioral health requires prioritizing patient confidentiality over convenient tracking tools.

Connecting Content Engagement to Inpatient Admission and Clinical Intake
The central financial breakdown in psychiatric marketing occurs between digital consumption and clinical intake. Marketing departments frequently report success using vanity metrics: impressions, total organic traffic, and top-of-funnel PDF downloads. Meanwhile, clinical directors, practice administrators, and intake supervisors face unfilled appointment slots, high no-show rates, and phone lines tied up with inquiries that fall outside the practice's clinical scope.
A functional mental health content program evaluates performance through downstream clinical metrics. Traffic volume is meaningless if readers are clinically mismatched with your practice's licensure, insurance panels, or geographic service area. To build an accountable conversion system, clinics must connect content touchpoints directly to verified patient interactions:
- Qualified Call Volume: Phone calls where prospective patients meet the practice's geographical boundary, age specialty, and clinical focus.
- Completed Intake Assessments: Initial diagnostic consultations or psychiatric evaluations that are scheduled, verified through insurance benefits checks, and confirmed.
- First-Appointment Adherence: Patients who transition from digital search to attending their initial psychiatric evaluation or therapeutic intake.
- Service Line Admission: For residential programs, partial hospitalization programs (PHP), or intensive outpatient programs (IOP), tracking organic engagement through to signed clinical admission.
Tracking patient acquisition down to clinical admission requires connecting phone tracking systems, CRM platforms, and practice management software through privacy-safe identifiers. When a prospective patient calls an intake line from a specialized clinical article, the call tracking infrastructure should capture the specific content topic that initiated the call while protecting the patient's identity. Intake teams should log the incoming inquiry with standard clinical descriptors, such as presenting condition, clinical service line needed, and insurance carrier.
Marketing Powered's founder managed marketing for a treatment network that grew from 3 to 24 locations, directing $1.5 to $2M per month in Google Ads across 11+ behavioral and mental health accounts. As a court-certified expert witness in advertising strategy, our approach insists that attribution must track to admission, not just initial lead generation. When reporting systems evaluate content performance by completed admissions rather than unvetted form submissions, practice owners can clearly see which clinical topics generate actual patient volume and which topics merely attract casual traffic.
Review our strategic framework on operational patient acquisition by exploring our guide to mental health practice marketing for multi-location groups.
A Reproducible Six-Step Clinical Review and Publishing Workflow
Maintaining editorial velocity while protecting clinical accuracy requires an explicit workflow. Without clear boundaries between creative writing and clinical governance, content creation stalls in committee review, or unverified copy slips through to publication.
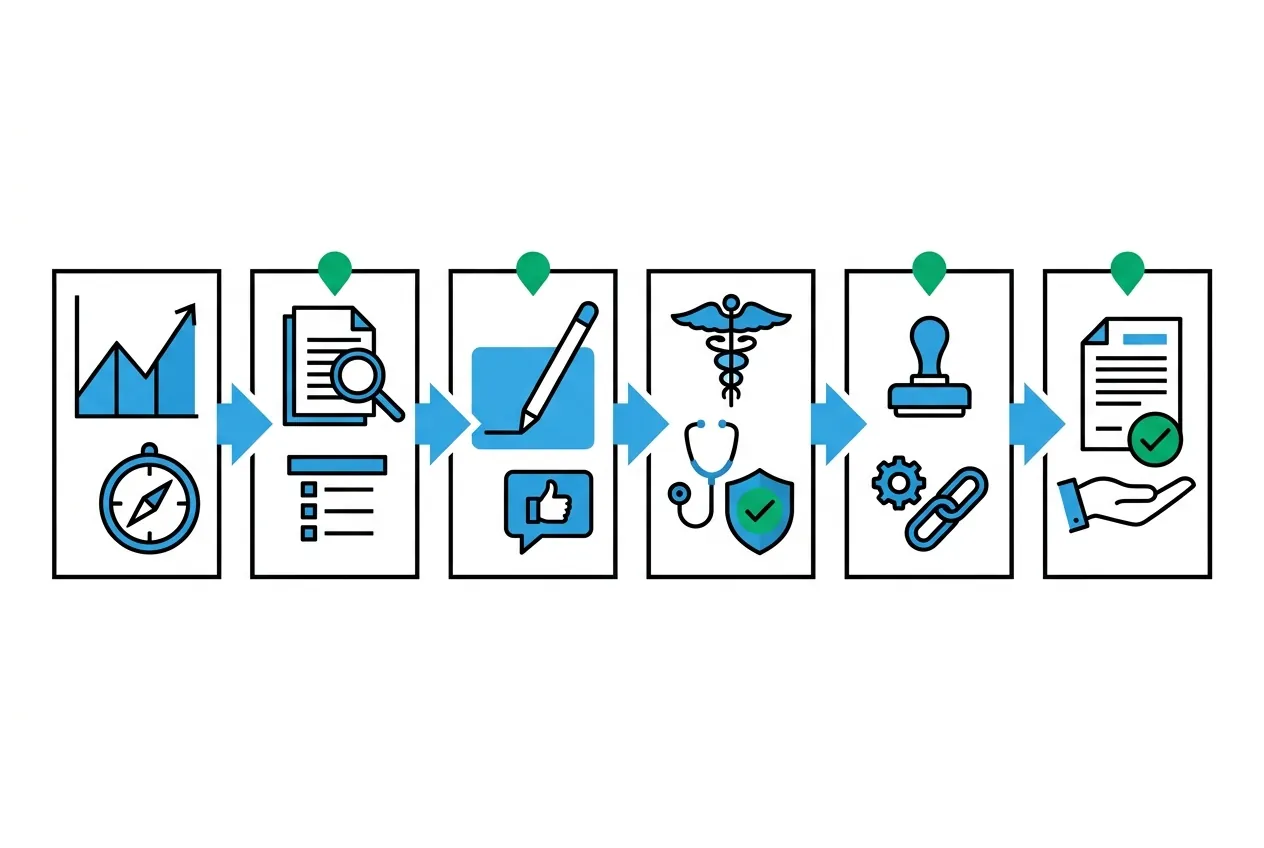
The following six-step editorial workflow provides a predictable operational pipeline for outpatient psychiatry groups and behavioral health clinics:
Step 1: Clinical Intent Identification
The marketing director identifies an underserved service line or patient inquiry trend in consultation with the clinical intake team. Target search topics are selected based on actual clinical offerings, accepted insurance coverage, and regional provider capacity, rather than generic wellness trends.
Step 2: Research and Outline Preparation
The content strategist drafts an outline detailing the clinical scope, target patient demographic, and differential diagnosis considerations. The outline cites standard clinical source material, such as the Diagnostic and Statistical Manual of Mental Disorders (DSM-5-TR), guidelines from the American Psychiatric Association, or published peer-reviewed studies.
Step 3: Production of the Initial Informational Draft
The writer develops the draft following compassionate, non-stigmatizing editorial guidelines. The content explains clinical conditions with operational precision, describes what happens during an initial appointment, and avoids absolute guarantees regarding treatment outcomes or recovery timelines.
Step 4: Credentialed Medical Review and Fact-Checking
A credentialed clinician (a board-certified psychiatrist, psychiatric nurse practitioner, or licensed clinical psychologist) conducts a medical review of the draft. The clinical reviewer assesses three non-negotiable points:
- Are medical claims and pharmacological references scientifically accurate?
- Does the content clearly distinguish between temporary emotional distress and diagnosable psychiatric conditions?
- Are appropriate crisis intervention resources included if the content touches acute distress?
Step 5: Editorial and Compliance Formatting
The editorial team implements the reviewer's clinical adjustments. The page is prepared with visible credentialing: the author's professional bio, the medical reviewer's full name, credentials, and state licensure, alongside a clear medical review badge. Schema markup is structured to convey author credentials directly to search engine crawlers.
Step 6: Clinical Sign-Off, Publishing, and Archival Review
The medical reviewer provides written approval before the article goes live on the practice website. The approved document is cataloged in an internal clinical review ledger with an assigned re-review date, typically set 12 to 24 months out, ensuring that clinical content remains current with emerging medical research and updated treatment protocols.
Email Us
Prefer to send the context directly?
Implementation Traps and Data Attribution Blind Spots
When clinics attempt to scale mental health content marketing without experienced guidance, operational breakdowns frequently occur. These mistakes inflate marketing expenses, create friction for intake staff, and obscure true return on marketing spend. Practice executives should audit their operations for the following common implementation traps:
Trap 1: The High-Volume Wellness Trap
Many digital agencies produce generic lifestyle articles covering topics like five breathing exercises to relieve stress or how to practice self-care at work. While these articles can generate casual social media shares, they rarely bring patients through the door. A person reading broad wellness tips is rarely looking for an immediate diagnostic assessment or intensive outpatient psychiatric care. Clinics spend thousands of dollars maintaining high-volume wellness blogs that generate zero qualified intakes, while their core clinical service pages remain unwritten and unranked.
Trap 2: Ungoverned AI Drafting Without Human Clinical Oversight
Automated artificial intelligence tools can summarize clinical literature, but relying on unassisted AI output creates severe clinical liabilities. Generic language models frequently introduce subtle pharmacological inaccuracies, misstate diagnostic criteria, or use outdated psychiatric terminology. Furthermore, search engines increasingly detect and discount generic, programmatic content that lacks demonstrated human expertise. Operating as an AI-native firm since 2022, Marketing Powered utilizes AI models to accelerate research, organize search data, and structure outlines, but licensed medical professionals must lead clinical verification and final editorial governance.
Trap 3: Disconnected Phone and Intake Tracking
A significant percentage of psychiatric patients will never fill out a digital form due to privacy concerns, emotional vulnerability, or immediate clinical urgency; they call the intake desk directly. When practices run content programs without dynamic, privacy-safe call tracking tied to specific content hubs, the marketing team cannot identify which articles generated the inbound calls. This leaves practice owners guessing whether their investment in educational content is producing tangible clinical value or simply consuming overhead.
Trap 4: Overlooking Local Physical Accessibility
Patients searching for psychiatric care ultimately require a provider who is licensed in their state and accessible either at a physical clinic or through compliant telehealth infrastructure. Producing broad, nationally focused mental health content without anchoring that content to specific state licensure, physical clinic locations, and regional insurance networks generates wasted inquiries. An intake team fielding 50 calls a week from patients living in states where the practice has no clinical license wastes valuable administrative capacity while delivering zero clinical encounters.
Questions, Answered.
Mental health clinics should implement a formal medical review protocol led by credentialed clinical staff, such as board-certified psychiatrists, psychiatric nurse practitioners, or licensed clinical social workers. Reviewers must cross-reference all diagnostic descriptions with the DSM-5-TR, confirm that medication discussions reflect FDA-approved indications or established off-label uses, and verify that all therapeutic descriptions clearly represent clinical evidence. Each published page should display the reviewer's full name, clinical credentials, state licensure, and the exact date of clinical approval.
Mental health content marketing should be evaluated through downstream clinical milestones rather than top-of-funnel web traffic or raw form submissions. Practices should deploy privacy-compliant, HIPAA-aware call tracking and intake logging that connects incoming patient inquiries to the specific content asset that originated the contact. Attribution models must evaluate performance based on qualified intake calls, scheduled clinical assessments, attended first appointments, and formal program admissions, rather than unvetted digital clicks.
No. Standard behavioral retargeting is strictly restricted in behavioral healthcare. Google Ads policy explicitly prohibits remarketing and personalized advertising based on sensitive health conditions, including mental health, addiction, and psychiatric disorders. Additionally, federal guidance from the HHS Office for Civil Rights restricts the deployment of third-party tracking pixels on healthcare websites where protected health information, such as IP addresses tied to health inquiries, could be exposed without patient consent.
While professional healthcare copywriters understand communication structure, tone, and search engine optimization, they do not carry medical licenses or legal responsibility for patient care. Clinical review by a licensed practitioner ensures that subtle diagnostic distinctions, safety considerations, and clinical boundaries are properly maintained. Furthermore, major search engines prioritize content that demonstrates transparent expertise, requiring credentialed authors and verified medical review stamps to rank competitively for sensitive health queries.
A medical reviewer for psychiatric content should hold active, unencumbered clinical licensure within the practice's relevant medical specialties. Appropriate credentials include Doctor of Medicine (MD) or Doctor of Osteopathic Medicine (DO) with board certification in adult, child, or adolescent psychiatry; Psychiatric-Mental Health Nurse Practitioner (PMHNP-BC); Doctor of Psychology (PsyD); Licensed Clinical Social Worker (LCSW); or Licensed Professional Counselor (LPC). The reviewer's professional background should align directly with the specific clinical service line discussed in the content. Request an acquisition audit
Ready to see where your marketing can improve?
Request a free audit of your paid media, landing pages, attribution, and measurement setup. You'll get a straight assessment of where the opportunities are.
or email us at info@marketingpowered.ai