Resources
How to Set a Rehab Marketing Budget by Admission Targets
A defensible rehab marketing strategy calculates financial investment by working backward from required monthly admissions, bed capacity, and payer mix rather than applying arbitrary percentages to top-line revenue. Because behavioral health providers face strict digital advertising regulations, banned remarketing audiences, and multi-step intake qualification processes, setting an accurate budget requires tracking unit economics from a qualified inquiry directly to a verified admission. This guide provides executive teams with the reverse-funnel math, channel allocation principles, and regulatory boundaries needed to build a highly accountable, admission-driven marketing budget.
By Mike Hulick, Founder, Marketing Powered

The Flaw of Percentage-Based Budgets in Behavioral Health
Standard corporate budgeting often dictates that a company should allocate a fixed percentage of projected gross revenue toward marketing and advertising. In traditional retail or software sectors, a flat allocation provides predictable pacing. In the behavioral health and addiction treatment sector, relying on a static boardroom spreadsheet disconnects capital deployment from the physical reality of the clinical facility. A treatment center marketing budget cannot be treated as a fixed overhead expense because the primary product constraint is real-time bed availability.
When executives lock their marketing spend to a top-line revenue percentage, they create structural inefficiencies. Consider a fully staffed residential facility operating at maximum capacity. If the marketing budget continues to spend aggressively based on historical revenue targets, the admissions department will generate inquiries for beds that do not exist. Intake coordinators are forced to turn away qualified individuals or place them on waitlists with high abandonment rates. The facility burns capital acquiring demand it cannot service.
Conversely, if census drops due to seasonal trends or a cluster of unexpected discharges, a percentage-based budget automatically shrinks just when the facility needs demand generation the most. Reduced revenue leads to reduced marketing spend, which leads to fewer admissions, creating a downward financial spiral.
Effective clinical marketing requires dynamic capital allocation. Spend must adjust based on scheduled patient discharges, open beds, facility clinical specialties, and immediate utilization needs. Setting a budget based on physical capacity aligns the marketing team, the admissions floor, and the clinical staff. It transforms the marketing department from an isolated cost center into a precise intake engine calibrated to keep the clinical facility operating at its optimal target census.

Reverse-Engineering Census by Bed Capacity and Length of Stay
Building a functional budget starts with clinical mathematics. To determine how much capital must be deployed, facility leaders must first calculate exactly how many admissions are required to sustain their target occupancy rate. This calculation relies on total licensed beds, the target occupancy percentage, and the Average Length of Stay (ALOS) for the specific level of care being marketed.
The foundational formula requires dividing the number of active beds by the ALOS, then multiplying by the days in the month. For example, a 60-bed residential facility with an average 30-day length of stay operating at a healthy 85 percent census target requires 51 active, occupied beds at any given time. Because the average patient stays for 30 days, the facility will see approximately 51 discharges per month. To maintain that 85 percent occupancy, the admissions department must secure 51 new admissions every single month.
Levels of care drastically alter this mathematical baseline. A medical detox facility experiences rapid patient turnover. A 20-bed detox program with an average length of stay of just 5 days turning at an 85 percent occupancy rate (17 active beds) must replace those 17 patients every five days. That requires approximately 102 admissions per month.
Despite having one-third the physical footprint of the 60-bed residential facility, the 20-bed detox center requires double the monthly admission volume. Consequently, the detox center marketing budget must be significantly larger or heavily optimized for high-velocity, immediate-intent search traffic. If the CFO applies the same budget to the detox center as the residential center based merely on facility square footage or flat historical data, the detox center will inevitably run empty.
A highly precise budget also accounts for premature bed churn, including patients who discharge Against Medical Advice or transfer to higher acuity care. Factoring in these variables ensures the marketing budget accurately reflects the required velocity of intake, establishing a clear commercial target for the marketing operations team.
Modeling Funnel Intake Mechanics and Conversion Drop-Offs
Once the required number of monthly admissions is established, the next step is modeling the intake funnel to determine how many raw inquiries are needed to yield those admissions. Behavioral health admissions are notoriously complex, requiring strict clinical evaluation and financial verification before a patient can physically enter the facility.
The intake process generally follows four distinct stages. The first stage is the raw inquiry, which includes every phone call, live chat, or secure web form generated by marketing efforts. The second stage is the qualified inquiry. At this point, the intake coordinator determines if the individual meets basic geographic criteria, possesses an accepted insurance policy or private funding, and matches the clinical capabilities of the facility. The third stage is the Verification of Benefits. The facility's utilization review or financial team contacts the commercial insurance payer to confirm out-of-network benefits, in-network contracted rates, deductibles, and out-of-pocket maximums. The final stage is the attended clinical intake, where the patient physically arrives at the facility, completes the assessment, and is officially admitted.
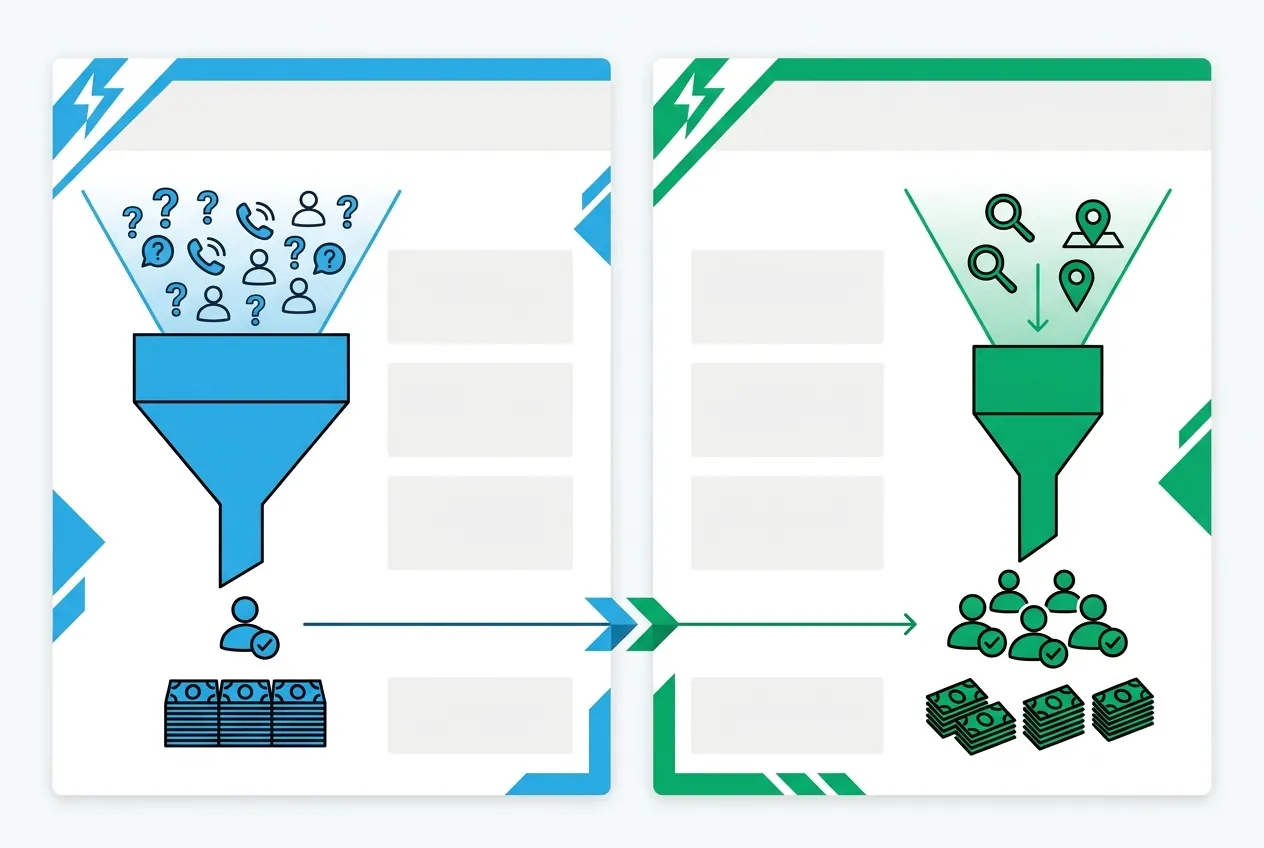
Significant conversion drop-off occurs at every stage of this sequence. A visual mapping of the intake coordinator’s workflow illustrates this friction. A digital marketing campaign might drive 1,000 clicks to a landing page, generating 150 phone calls. Of those 150 raw callers, only 45 might be qualified, as the rest could be seeking Medicaid programs the facility does not accept or out-of-state resources. Of the 45 qualified callers, the financial team might successfully verify and approve benefits for only 20 individuals. Of those 20 approved candidates, only 10 might physically arrive at the facility and complete the admission process.
In this scenario, a 150-call pipeline yields 10 admissions. If the facility requires 50 admissions per month, the marketing strategy must be funded and engineered to generate 750 phone calls of identical quality. Understanding these specific funnel mechanics is critical. If leadership attempts to reduce the marketing budget by purchasing lower-quality, broad-match search traffic, the raw call volume might remain high, but the clinical qualification rate will plummet. The intake floor becomes overwhelmed with unserviceable inquiries, staff burnout accelerates, and actual clinical admissions drop.
Free Audit
Want a straight read on where your budget is leaking?
Navigating Platform Regulations and Healthcare Advertising Policies
Funding a digital acquisition strategy in the behavioral health sector requires navigating severe regulatory and platform-level constraints. General consumer marketing tactics are often explicitly banned when applied to addiction treatment and mental health. A defensible budget must account for the high cost of compliance and the technical limitations imposed on healthcare advertisers.
Major advertising networks enforce rigid boundaries around patient privacy. Google Ads strictly bans retargeting and remarketing lists based on sensitive healthcare categories, including substance abuse treatment and mental health conditions Google Ads Healthcare Policy. In traditional B2B or e-commerce marketing, advertisers rely on tracking pixels to serve follow-up advertisements to users who visited their website but did not convert. Because behavioral health advertisers cannot use this tactic, they lose the standard sequence of follow-up impressions.
Without a remarketing safety net, treatment centers must convert prospective patients on the very first touchpoint. This requires a heavier budget allocation toward high-intent paid search, technically flawless landing pages, and rapid intake response times.
Furthermore, platform certification acts as an absolute gatekeeper for paid media deployment. Google requires advertisers promoting addiction services in the United States to obtain specific authorization before their ads are permitted to serve Google Ads Addiction Services Policy. This authorization requires independent vetting of the facility's clinical licensure, leadership credentials, and marketing transparency LegitScript Addiction Treatment Standards. Navigating the certification interface, managing the warning labels in the ad platform, and maintaining compliance require dedicated operational resources that must be factored into the overall strategy.
Data privacy enforcement further complicates the technical marketing stack. Regulated entities cannot deploy tracking pixels or third-party marketing technologies that transmit protected health information to unauthorized vendors without proper business associate agreements and HIPAA-compliant execution. See HHS guidance on online tracking technologies. Budgeting for compliant architecture ensures that the facility can measure campaign performance without risking severe regulatory penalties or compromising patient privacy.

Measuring Cost Per Admission Over Cost Per Lead
To maximize the efficiency of a treatment center marketing budget, executive teams must abandon Cost Per Lead as their primary metric of success. Optimizing a campaign purely for cheap inquiries inevitably drives the algorithms to find the lowest-barrier traffic, resulting in clinically unqualified calls that waste intake resources.
The only metric that accurately dictates the financial viability of a marketing campaign is the cost per admission. Shifting focus to this metric requires connecting marketing data to clinical outcomes. If a campaign generates 100 leads at $50 each, the initial spend is $5,000. If only one lead admits, the cost per admission is $5,000. Conversely, a highly targeted campaign might generate only 20 inquiries at $200 each, requiring $4,000 in spend. If five of those inquiries admit, the cost per admission is $800. The second campaign is vastly more expensive on a per-click and per-lead basis, yet it is significantly more profitable for the facility.
Tracking this requires full-funnel attribution. The marketing architecture must capture the specific search term, ad campaign, and geographic origin of the initial digital touchpoint, then map that exact session to the final clinical admission record in the CRM. By tracking attribution directly to admission rather than just the initial lead, facility leaders can definitively identify which marketing channels produce verified revenue and which channels simply produce noise.
This level of measurement ensures that the CFO and the CMO are speaking the same financial language. When marketing requests additional budget, they are not asking for money to buy clicks. They are presenting a mathematically sound request to fund a specific number of anticipated clinical admissions based on historical conversion data.
Framework for Building an Admission-Driven Marketing Budget
Building and executing this type of strategy requires highly deliberate data architecture and operational discipline. The framework for an admission-driven marketing budget relies on aligning the executive suite, the technical infrastructure, and the intake floor.
The physical process begins with a concrete data audit. Leadership must evaluate the current local hardware servers, cloud environments, and CRM dashboards to ensure marketing touchpoints are actually visible alongside intake records. Marketing Powered has been AI-native since 2022, utilizing owned, local AI infrastructure for HIPAA-aware inference. This specialized hardware capability allows organizations to process complex admission variables and marketing data without exposing sensitive information to public cloud networks. This technical foundation ensures that precise attribution remains a mathematical reality rather than an unfulfilled software promise.
Operational frameworks require practical testing. The foundation of this approach relies on structural lessons learned by a former healthcare CMO who ran marketing for a treatment network that grew from 3 to 24 locations. Having managed $1.5 to $2M per month in Google Ads across 11+ behavioral and mental health accounts, the fundamental lesson is that scale requires extreme precision.
To execute this framework, follow these structural steps:
- Calculate Required Admissions: Define the exact number of monthly admissions needed per facility based on active beds and historical length of stay.
- Establish the Baseline Conversion Rate: Audit the previous 90 days of intake data to determine the true drop-off percentage from raw inquiry to clinical admission.
- Determine Target Acquisition Costs: Work with the finance department to establish the maximum allowable cost per admission based on average revenue per patient by payer mix.
- Deploy Compliant Infrastructure: Configure tracking systems that map initial digital touchpoints to finalized CRM admissions without violating platform privacy rules or federal healthcare regulations.
- Fund by Capacity: Allocate digital marketing capital specifically to generate highly targeted inquiries that match the facility's open beds, dynamically scaling spend up or down based on the live clinical census.
Furthermore, as a court-certified expert witness in advertising strategy, the founder of Marketing Powered leverages this perspective to identify exactly where media capital is wasted on non-compliant or unmeasured tactics. Establishing this strict measurement framework prevents budget bleed and ensures every dollar deployed serves the clinical census.
Questions, Answered.
A rehab marketing budget should be determined by total licensed bed capacity, the target facility occupancy rate, and the average length of stay for the specific level of care. These clinical metrics define the required monthly admission velocity. Financial inputs include the historical cost per admission by channel, the facility's accepted payer mix, and the conversion drop-off rate between initial inquiry, verified benefits, and physical intake.
Digital platforms enforce strict privacy guidelines for healthcare advertisers. The inability to use remarketing audiences means behavioral health facilities must convert users on the first interaction, which generally increases the initial cost per click and cost per acquisition. Additionally, mandatory verification processes require operational time and resources to maintain compliance across active search campaigns.
Cost per lead measures the efficiency of generating a raw phone call or form fill, regardless of the user's clinical eligibility or insurance status. Cost per admission measures the financial efficiency of placing a verified, qualified patient into a clinical bed. Optimizing for cost per lead frequently results in overwhelming intake staff with unqualified volume, whereas optimizing for cost per admission protects facility margins and clinical integrity.
Strategy should be measured using closed-loop attribution that connects the initial marketing touchpoint to the final CRM disposition. Measurement must track the progression from raw call to qualified call, noting exactly which campaigns yield inquiries that pass clinical and financial verification. Request an acquisition audit
Ready to see where your marketing can improve?
Request a free audit of your paid media, landing pages, attribution, and measurement setup. You'll get a straight assessment of where the opportunities are.
or email us at info@marketingpowered.ai