Resources
Behavioral Health Marketing Strategies for Operators
A practical way to organize marketing strategies for behavioral health is to work through dependencies before scaling channels. Define a qualified admission, instrument every call and form into the CRM, and tighten intake and benefits verification. Only then expand paid search, local visibility, and referral work, and measure against qualified calls and verified admissions where authorized data allows.
By Mike Hulick, Founder, Marketing Powered

What an effective strategy includes
Picture a Monday census meeting at the program. The admissions director has a board of people who arrived. The marketing lead has the call report for the same week. One row is a parent who searched for residential substance use disorder care, reached voicemail after hours, and was counted as a lead. That person is not on the census board. Behavioral health marketing that stops at the call cannot explain the gap.
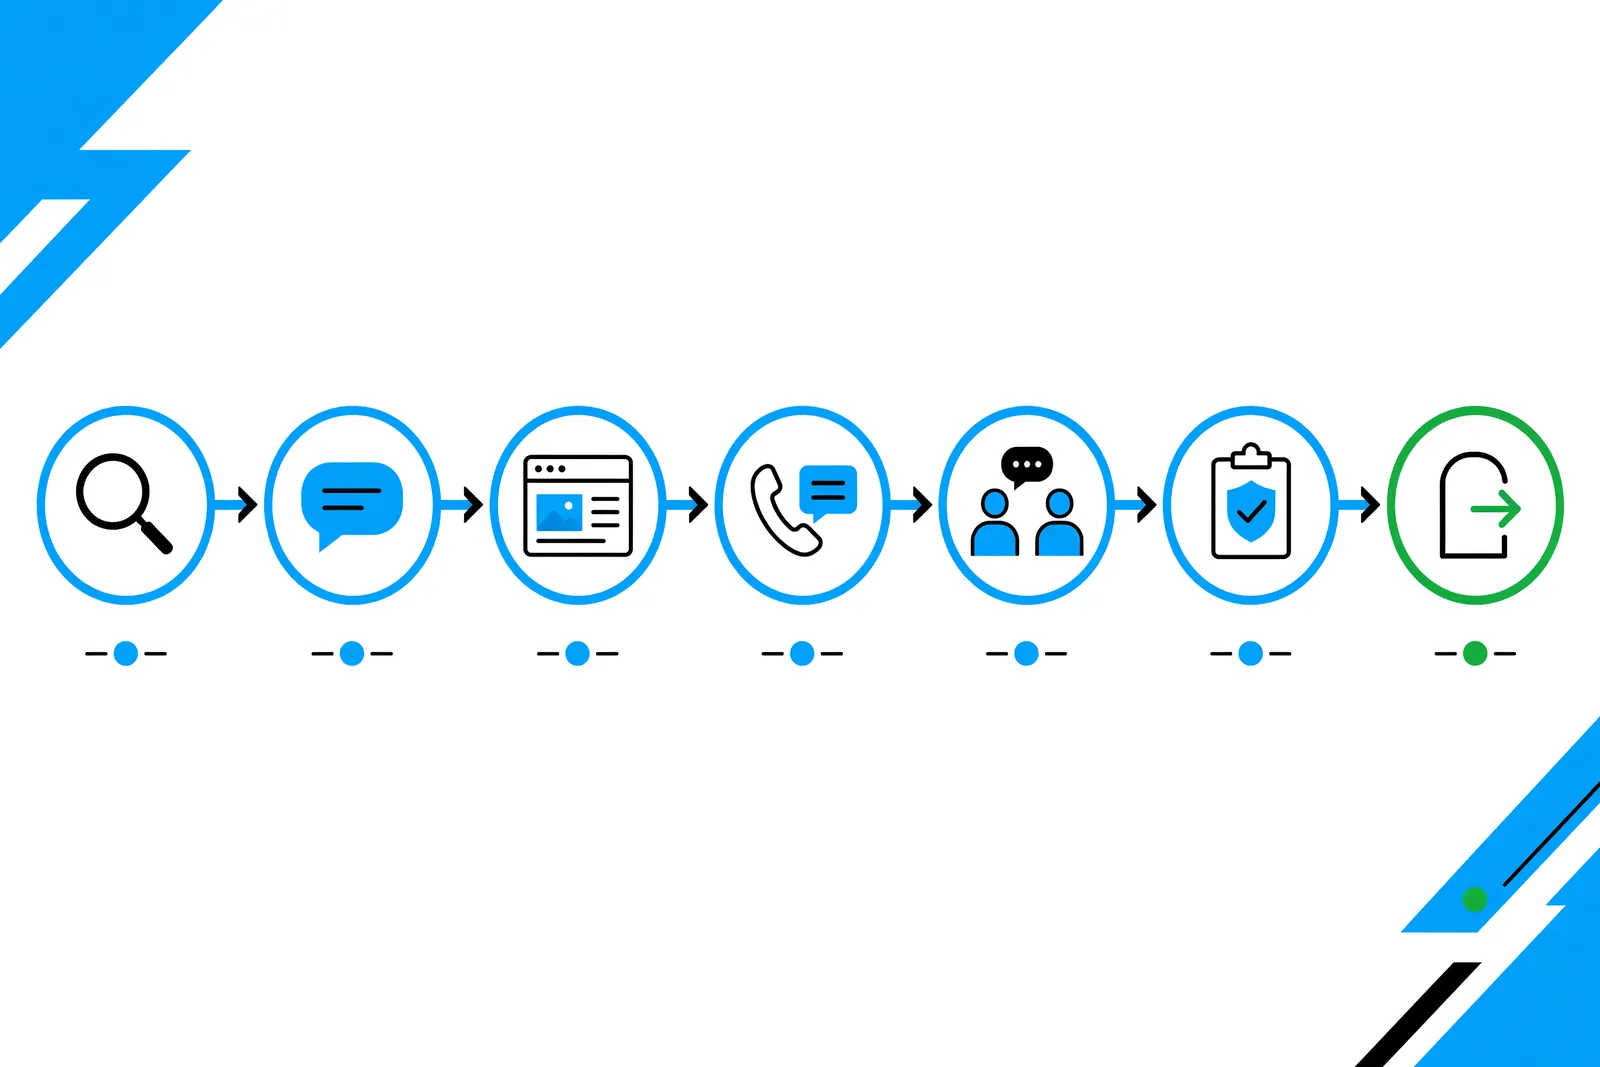
Treat the strategy as the full acquisition chain, not the ad account:
- Demand: a person or family searches, asks a referrer, or sees a message.
- Message: what the ad, listing, or page says.
- Landing page or listing.
- Call or form.
- Intake conversation.
- Benefits verification and level-of-care fit.
- Admission.
Reporting that stops at the inquiry cannot show what happened during intake, verification, or admission. Investigate those handoffs alongside media performance. The ad may attract people who need a level of care the facility does not offer. The tracking number may not pass source data into the CRM. Intake may return the call after the person has reached another program. Verification may show an out-of-network plan only after two conversations.
Acquisition performance is capped by the weakest stage in a chain you can measure: qualified definition, tracking, intake conversion, capacity, and payor fit. Channel work pays off after those stages are instrumented. Sequence the work by dependency. Each stage below has an owner, a measure, and a failure signal.
When these strategies apply
The sequence works for outpatient, intensive outpatient, partial hospitalization, residential, and inpatient programs, in mental health and substance use disorder care. The operating details change with the program.
Adapt qualification criteria, messaging, and intake steps to each service line. A residential substance use disorder program and an outpatient therapy group have different timelines, payors, and first conversations. Build each path on its own.
Single-location programs can run one chain. Multi-location operators need measurement by facility and by service line. A pooled report hides the site where intake is slow or where capacity is full. The same unit-level view applies when a hospital service line or another regulated organization acquires demand by location.
Encode payor fit in the qualified definition when census depends on specific commercial networks, Medicaid, or private pay. Otherwise the report will count demand the program cannot serve.
Do not increase acquisition spend solely to generate immediate admissions when the relevant service lacks capacity. Evaluate future openings and other service lines before moving budget. A residential unit with no near-term bed should not keep buying clicks for that unit. People seeking care get a waitlist or a missed return call, and the spend does not become an admission.
This page is an operating sequence. It is not clinical guidance, legal advice, or a substitute for the current platform policy. Use your own baseline. This guide does not prescribe industry conversion benchmarks.
Seven strategies in dependency order
1. Define a qualified admission
Write the definition and have marketing and admissions sign the same version. Cover level of care, payor fit, geography or willingness to travel, readiness to seek care now, and reachability. A general information request is not the same event as a person or family seeking care this week.
Use tiers if you need them: qualified call, qualified verified inquiry, and admission. Each tier gets a written rule and one owner who can change it. The admissions leader owns the definition. The marketing leader is accountable for using it in reporting. Failure signal: the two teams produce different counts for the same week.
2. Build the measurement layer
Later decisions depend on this layer. Track calls with source attached. Write forms into the CRM or intake system, not only an inbox. Name every channel the same way. Hold fields for the qualified definition, disposition, level of care requested, payor, verification result, and admission status. Define what is collected, who can see it, and how long it is kept.
Use recordings only where applicable law and organizational privacy controls permit them, with required consent, restricted access, and defined retention. Federal wiretap law includes a one-party consent route, with conditions: a person not acting under color of law may intercept a wire, oral, or electronic communication if that person is a party, or if one party has given prior consent, unless the interception is for a criminal or tortious purpose (18 U.S.C. § 2511). Florida separately makes interception lawful for a person when all parties have given prior consent (Florida Statutes § 934.03). Those two sources are not a nationwide script. Review the design with counsel before launch.
Keep patient-level attribution inside approved systems. Do not assume that a coded event is safe to send to an advertising platform. Assess what the recipient can infer and whether disclosure is permitted under applicable privacy requirements, including HIPAA where it applies, before launch. No workflow makes the setup compliant by itself.
Records related to substance use disorder diagnosis, treatment, or referral may be subject to additional federal privacy rules, including 42 CFR Part 2 where applicable. Review any flow of intake or tracking data with privacy counsel before it leaves the systems you control.
Where infrastructure control matters, it matters because you can set where analysis runs and which privacy boundaries apply. Configuring compute is separate from who owns the data. It does not mean every workload runs locally.
Owner: marketing operations, or the outside team doing that work, with a named internal data steward. Failure signal: an admission cannot be traced to the first tracked touch within what authorized data permits.
3. Fix intake and verification
Review intake before you raise budget. Match coverage to the hours ads run and people search. Set a response target for forms and name the owner. The first conversation should identify level of care, payor, and urgency without turning into an interrogation. Time benefits verification, name who does it, and decide what the person hears while they wait. Schedule the next clinical step before the call ends when the person is ready. Document a respectful follow-up path for people who are not ready now.
A structured review of a sample of calls and notes can reveal intake friction that aggregate reporting misses. Review that sample with admissions on a set cadence. Owner: admissions director. Failure signal: qualified inquiries stall between first contact and verification.
4. Match the page to the level of care
Each page should state the level of care and the population served in plain language. Use "people seeking care" and "substance use disorder." Avoid labels that define a person by a condition. Make the next step a call or an intake form. Show accepted insurance accurately and keep it current. Do not imply treatment outcomes or efficacy. Clinical and compliance leads should review claims.
Create distinct pages where services and visitor needs differ, then test qualified inquiry performance in your own data. Owner: marketing leader, with a clinical reviewer. Failure signal: calls for services the facility does not offer.
5. Run paid search and local presence within policy
Paid search and local listings capture intent that already exists. Use them as a scale step after earlier stages can absorb the demand. Structure campaigns by level of care and location. Exclude services you do not provide. Report qualified calls, not clicks alone. Keep listings, hours, services, and phone numbers consistent. Use responses that do not confirm patient relationships or disclose treatment information.
Google restricts advertising for drug and alcohol addiction services in the United States. Some recovery-oriented services may require third-party certification before they can advertise, while other related services are ineligible. Confirm current eligibility and certification requirements on Google’s policy pages before launch. Recheck the policy page before launch and record the date you read it.
Health-related content, including mental health and addiction services, may fall under sensitive category restrictions on Google Ads. Advertiser-built audiences, lookalikes, or Customer Match lists may be restricted when they could contain sensitive user signals. Verify the current policy before using any audience targeting. Do not assume a remarketing list built from your own data is available.
Multi-location accounts should show spend, calls, and admissions by facility. Owner: paid media lead. Failure signal: budget rises while qualified calls per location stay flat or fall.
6. Track referrals and reputation
Referrals from clinicians, hospitals, employers, schools, and community organizations can be a durable source of qualified admissions. Referral attribution needs an explicit source field and a consistent intake process. Use a dedicated line or form per relationship, log the source at first contact, and tell the referrer who to call, what to send, and when they will hear back.
Use a voluntary, neutral review-request process that does not screen by satisfaction, offer incentives, or pressure people to disclose treatment. Google’s policy does not allow merchants to discourage or prohibit negative reviews or selectively solicit positive reviews (Google Maps user content policy). Never confirm treatment status in a public response. Have compliance review the request process before it is used.
Owner: business development or community liaison. Failure signal: referral volume cannot be separated from direct or unknown.
7. Scale only through open gates
Before spend rises, confirm three gates. Measurement: the channel reports qualified calls and admissions to the same standard as the others. Intake: the team can absorb added volume without missing the response target. Capacity and payor: open beds or slots, and the payor mix, support more admissions at that level of care.
If a gate is closed, fix it first. If all three are open, increase spend in controlled steps and review qualified calls and admissions after each step. Decide in advance what result would make you hold or reverse. Owner: the COO or CEO, who can see all three gates. Failure signal: spend is approved on cost per lead alone.
Free Audit
Want a straight read on where your budget is leaking?
Who owns each stage
Put the admissions director, the marketing lead, and the COO in the same weekly review, each with the report they actually use. One person has the call log. One has verification status. One has open beds or open appointment slots. The review fails when those documents use different definitions of the same person. The matrix is the comparison to keep in that room. It assigns the decision, not the task list.
- Qualified admission. Accountable owner: Admissions leader. Primary measure: One written definition used by both teams. Failure signal: Different counts for the same week.
- Measurement. Accountable owner: Marketing operations, with a data steward. Primary measure: Share of inquiries traced to source. Failure signal: Admissions with unknown source.
- Intake and verification. Accountable owner: Admissions director. Primary measure: Time to first contact and verification completion. Failure signal: Stalls before verification.
- Message and pages. Accountable owner: Marketing leader, with a clinical reviewer. Primary measure: Qualified rate by page. Failure signal: Calls for services not offered.
- Paid search and local. Accountable owner: Paid media lead. Primary measure: Qualified calls by location. Failure signal: Spend up, qualified calls flat.
- Referral and reputation. Accountable owner: Business development. Primary measure: Referral-sourced admissions. Failure signal: Referrals reported as unknown.
- Scaling. Accountable owner: COO or CEO. Primary measure: Gate status. Failure signal: Spend approved on lead cost alone.
Some operators run the sequence in-house. Some use an outside team. Many split it. If you bring in help, ask who owns each stage, how call and admission data reach the same report, what the team needs from admissions, and how sensitive data stays inside approved systems. Ask what the partner will not do. The scope of this work with treatment organizations is described for behavioral health organizations. The work focuses on acquisition, intake handoffs, and attribution, using the evidence available.

A worksheet for the constraint
Use this on one level of care and one location for a recent closed period. It is illustrative. It uses variables, not benchmarks, and it is not a case study. Pull the figures from the CRM, not from the ad platform alone.
Define L, Q, V, and A as deduplicated people from the same inquiry cohort. State the admission follow-up window in writing. Report admissions from older inquiries separately. Do not mix them into A.
Inputs.
- S = marketing spend in the period for that location and level of care
- L = deduplicated people who called or submitted a form in the cohort
- Q = people in that cohort who meet the written qualified definition
- V = people in Q with completed benefits verification
- A = people in that cohort admitted inside the stated window
- A_prior = admissions in the period from older inquiries, reported separately
- K_beds = open beds in the next period, if the service uses beds
- K_slots = open appointment slots in the next period, if the service uses slots
Calculations.
- Qualified rate = Q / L. If L is 0, mark not calculable.
- Verification rate = V / Q. If Q is 0, mark not calculable.
- Admission rate = A / V. If V is 0, mark not calculable.
- Cost per qualified inquiry = S / Q. If Q is 0, mark not calculable.
- Cost per admission = S / A. If A is 0, mark not calculable.
- Estimated inquiries needed to fill beds = K_beds / (A / Q). Use this only when A and Q are both greater than zero. Label it an estimate. It depends on a positive historical conversion rate and on future conditions comparable to the period you measured. If the rate is zero or not calculable, do not produce a number. Run a separate estimate for slots. Beds and appointment slots are different capacity definitions.
How to read it.
Compare each rate with your own prior periods and with the admissions target. This guide does not prescribe industry conversion benchmarks. Use gaps against your own target to identify candidate constraints, then test which change could improve admissions within available capacity. Under the model's assumptions, if estimated inquiries needed are lower than inquiries already received, current volume may be sufficient. Investigate conversion, timing, and capacity before increasing spend. If the estimate is much higher, check the measurement and intake gates before raising spend. Run the worksheet by location, level of care, and channel. A blended figure hides the break. If V or A cannot be filled in, the measurement layer is the first project.
Mistakes and limits of the data
Cost per click and cost per lead describe activity. They do not describe admissions. If marketing counts forms and admissions counts census, the gap belongs to no one. The owner matrix exists so that gap has a name.
Platform and privacy rules change. Open the source, record the date you read it, and have counsel review anything that moves information about a person seeking care. More demand into a slow intake process, or into a service with no near-term openings, does not by itself produce more admissions. More tracking is not better tracking. Collect what supports a decision.
Attribution links a first tracked touch to an outcome inside the data you are allowed to use. It does not prove that a channel caused the admission, especially when a person calls more than one program or searches several times before acting. Referral and word-of-mouth effects can sit outside the tracked set. Treat that as a measurement limit, not as evidence that those paths did nothing. A single location can move a lot from one month to the next. Report estimates as estimates and measured facts as measured facts. Use a controlled change when you need evidence about cause.

Email Us
Prefer to send the context directly?
Implementation checklist
Use this checklist with your admissions leader. Walk it at the program, not only in a slide review. Stand with marketing operations at the phones that appear in ads and listings, open the form that should write to the CRM, and check the fields admissions actually completes.
- Written qualified admission definition, signed by marketing and admissions
- Tiers defined: qualified call, qualified verified inquiry, admission
- Call tracking on every number used in ads, listings, and referral lines, with consent handled under applicable law
- Forms writing to the CRM or intake system, with source captured
- Campaign naming documented and applied
- CRM fields for disposition, level of care, payor, verification, and admission
- Privacy and consent review completed with counsel, including Part 2 where it applies
- Intake coverage aligned to the hours when people seek care
- Response targets set for calls and forms, with a named owner
- Sample review of calls and notes on a set cadence
- Distinct pages where levels of care differ, with current insurance information
- Google addiction-services certification and sensitive-audience rules checked on the current policy pages, with the retrieval date recorded
- Neutral review requests, with no screening by satisfaction and no public confirmation of treatment
- Referral source field or line for each referral relationship
- Reporting by location, level of care, and channel
- Measurement, intake, and capacity gates reviewed before any spend increase
Questions, Answered.
Start with this operating sequence rather than a channel list. Define who can be admitted, measure that definition through intake, and scale a channel only after measurement, intake, and capacity can absorb the demand.
Count inquiries against a written qualified definition, then follow the same people through verification to admission inside a stated window. Report cost per qualified inquiry and cost per admission by location, level of care, and channel. Use authorized data only, and review what moves between systems with counsel. Where a call cannot be linked to an admission, report the gap. Do not fill it with an estimate. Marketing for behavioral health that reports only leads leaves the admissions question unanswered.
The sequence can be used for both. Qualification rules, payor mix, intake scripts, and platform requirements differ, so build each separately. Google's addiction-services certification rule covers recovery-oriented drug and alcohol advertising. It is not a blanket rule for every mental health campaign.
Do not increase acquisition spend solely to generate immediate admissions when the relevant service lacks capacity. Evaluate future openings and other service lines before moving budget. Request an acquisition audit
Ready to see where your marketing can improve?
Request a free audit of your paid media, landing pages, attribution, and measurement setup. You'll get a straight assessment of where the opportunities are.
or email us at info@marketingpowered.ai